


Everything you need to know about your shoulder’s glenoid and labrum anatomy
By Dr. Gregory Drake
Serving Elk Grove Village, Hoffman Estates, and the Northwest Chicago Suburbs
Normal
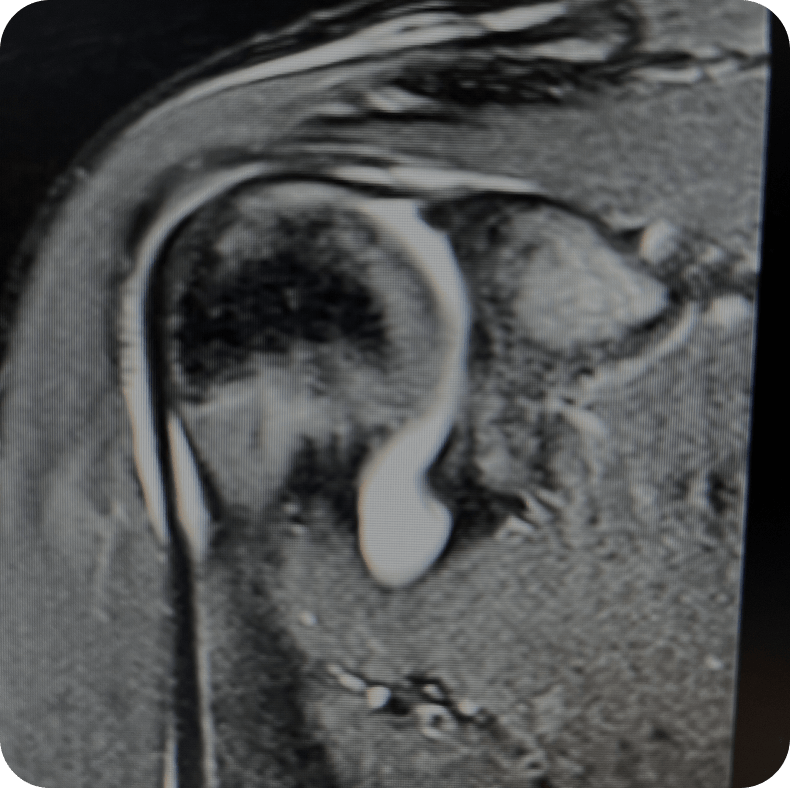
Labrum Tear

What is the Shoulder Labrum?
The labrum or glenoid labrum is the cartilage surrounding the socket of the shoulder, otherwise known as the glenoid. The labrum lies along the glenoid’s perimeter, much like the bumper on a bumper car. The labrum provides stability to the shoulder and also serves superiorly as the attachment of the biceps tendon.
When a shoulder dislocates, the anterior labrum typically tears. If the shoulder experiences repetitive overhead use such in throwing athletes or volleyball players, a superior labral (SLAP) tear can occur. If the labrum tears, it can lead to feelings of instability and pain.
Safe and Effective Shoulder Labrum Tear Surgery In Chicago
Living with shoulder pain can be agonizing. Having to carry out daily activities with pain, weakness, and instability in the shoulder is a daunting task. But that pain doesn’t have to be permanent. Consult with Dr. Gregory Drake to see if you may have a tear and if a labral repair could help.
Athletes who compete in sports that involve the frequent use of their shoulders can be prone to shoulder labral tears. If a labrum tear is left untreated, it can cause chronic pain and, in worse cases, lead to locking of the shoulder and feelings of instability, which can cause intense pain when you move your shoulder.
One of the reasons patients shy away from getting surgery is because they don’t know the success rate or they need a trustworthy doctor.
Dr. Gregory Drake is an expert orthopedic shoulder specialist in Chicago. He performs hundreds of shoulder surgeries each year and many include treating SLAP tears and anterior labral repairs following dislocations.
If you have a known SLAP tear, Bankart tear or have feelings of instability in your shoulder, come visit Level Up Shoulder and Dr. Drake can guide you through the anatomy, and the treatment to put you on the right course for improvement. If you or someone you know have had an injury involving the glenoid labrum, and are seeking treatment near Chicago or Chicagoland area, schedule an appointment today.

Types of Shoulder Labrum Tears
There are multiple types of labrum tears, with differences based on the type of injury and location at which the labral tissue detaches. Diagnosing a labral tear will involve the use of injecting specialized dye into the joint before the MRI scan, allowing Dr. Drake to see more detail in the imaging of the joint. The two most common shoulder labrum tears are SLAP labral tears and bankart tears. They can both cause pain and an inability to move the shoulder properly.
SLAP Labral Tears
A SLAP tear or SLAP lesion known as a “Superior labrum, anterior to posterior,” simply means a labral tear that occurs at the upper part of the labrum where the long head of the biceps tendon attaches inside the shoulder joint. It is common among baseball, volleyball or tennis athletes who engage in repetitive and high energy overhead arm motions. If you have a SLAP tear and you need SLAP repair, reach out to Dr. Drake at Level Up Shoulder and he would be happy to educate, diagnose and treat your shoulder condition.
Bankart Tears
Bankart tears or lesions involving the anterior labrum are more common in young people with a history of a shoulder dislocation. It is a labral tear in the anterior (front) and inferior (lower) half of the glenoid. It is caused by a traumatic force that detaches the labrum (cartilage) from the glenoid (bone) as the ball moves out of the socket. This causes the shoulder to become unstable as a result of the tear, as the labral tissue is no longer able to buttress the humeral head, subjecting the shoulder to another dislocation.
Shoulder Labrum Tears Treatments and Surgery
Labrum tears can be treated in two ways: Surgical and non-surgical treatments. Before deciding what treatment is best for you, Dr. Gregory Drake will perform a diagnosis for you where he will ask you a series of questions about the events that led to your labrum tear and also test your shoulder pain level, motion, and stability.
Non-surgical treatment
If the diagnosis shows that the labrum tear is not severe. Dr. Gregory may prescribe non-surgical treatments like:
- Avoiding certain activities at home and work
- Anti-inflammatory drugs
- Physical therapy
- Corticosteroid or Platelet-Rich Plasma Injections
Surgical treatment
If your labrum tear requires surgery, Dr. Gregory will treat it with minimally invasive surgery, which is his specialty. This surgery involves the removal of the damaged labrum and cartilage to enable the easy movement of the joint. This arthroscopic surgery is used to perform different types of shoulder labrum tear surgery:
- SLAP repair
- Debridement
- Biceps Tenodesis
- Labrum repair
Recovery Time After Surgery
After surgery, it is advised to wear a sling on your arm for up to a month to keep the shoulder immovable. Then you might have to undergo physical therapy to gradually stretch and strengthen the shoulder muscles.
Shoulder Labrum Tear Surgery typically takes nine months to 1 year to heal and about six months to get back to using your shoulder correctly, especially if you play sports that require energetic overhead arm motions.
Frequently Asked Questions
Do I need surgery for this condition?
Not always. If the tear is mild, non-surgical options like activity modification, anti-inflammatory medications, physical therapy, and injections may be effective. Surgery is typically recommended for significant instability, repeated dislocations, or when conservative care has not provided lasting relief.
What if my MRI doesn't match my symptoms?
This is especially relevant for labral tears. A standard MRI can miss them entirely. Diagnosing a labral tear typically requires a contrast MRI, where specialized dye is injected into the joint before the scan to allow for greater detail. If your standard MRI came back normal but your symptoms suggest a tear, a contrast study may be the missing piece.
What should I expect after an arthroscopic rotator cuff surgery?
Following an arthroscopic rotator cuff surgery, you will be discharged the same day. A sling will be worn for 6 weeks, with pendulum exercises beginning on the first day after surgery. Pain medication, Tylenol and ice will be utilized to treat the pain and swelling. At 2 weeks after surgery, formal physical therapy will commence. One cannot actively use the shoulder for lifting, pushing, or pulling for 3 months following surgery, however, use of the hands for typing and light use can start immediately following the procedure. Driving may start once pain medications have been stopped. Full healing can take 6 months to a year.
What happens if I wait?
An untreated labral tear can lead to chronic pain, shoulder locking, and ongoing instability. For patients with a history of dislocations, leaving the tear unaddressed increases the risk of repeated dislocations, which can cause further joint damage over time.
How long does an arthroscopic rotator cuff surgery take?
Patients will need to arrive at least one hour prior to surgery. Surgical times vary depending on the severity of the tear, however, most repairs take less than 40 minutes. About an hour will be spent in the recovery room, prior to discharge.
Can this heal without surgery?
Mild labral tears may improve with non-surgical treatment. However, once the labrum has detached from the bone — as in a Bankart tear — it cannot reattach on its own. Structural repairs of that kind require surgery.
What if physical therapy didn't work?
Physical therapy can help manage symptoms, but it doesn’t repair structural damage to the labrum. If instability or pain persists despite PT, surgical repair is often the most appropriate path forward.
What are exercises for the rotator cuff after an arthroscopic repair?
Pendulum exercises are started immediately following the procedure. At 2 weeks following the procedure, formal physical therapy will begin. Passive range of motion is initiated and continues until the three-month mark. At that time, active range of motion of the shoulder may begin. The physical therapist will also begin strengthening the shoulder at 3 months following the repair.